Can Food Allergy Immunotherapy Help Severe Food Allergies?

For years, managing food allergy meant one thing:
Avoid the food.
Parents became expert label readers.
They checked restaurant menus.
They asked, “Does this contain milk? Egg? Peanut? Nuts?”
And they carried adrenaline everywhere — just in case.
For a child with a severe food allergy, eating can sometimes feel less like enjoying a meal and more like managing a risk.
But what if we could do more than avoidance?
What if we could train the immune system to become less sensitive to the food?
That is the idea behind food allergy immunotherapy.
And the way we approach food allergy is changing.
Think of Food Immunotherapy Like Exercise

I often explain immunotherapy this way:
Your immune system needs training.
Imagine you haven’t exercised for years.
The first time you go for a run, your heart races.
You’re short of breath.
Your muscles ache.
You probably don’t think:
“My body is broken.”
You think:
“My body isn’t used to this.”
With gradual training, your body adapts.
Food immunotherapy works on a similar principle.
We introduce the allergen in very small, carefully controlled amounts and gradually increase the exposure.
Over time, the immune system may become less reactive.
But there is one very important difference:
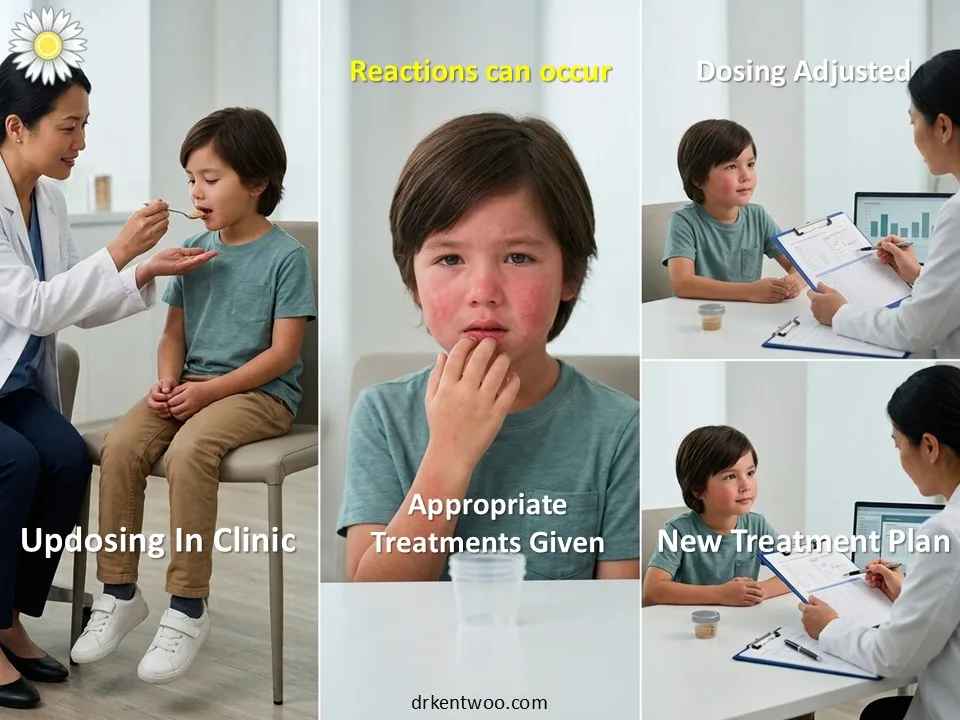
We never push through an allergic reaction.
If symptoms occur, we assess them carefully and adjust treatment as needed.
This is why food immunotherapy needs medical supervision.
SLIT: Start Very Small

For some highly allergic patients, we may start with Sublingual Immunotherapy (SLIT).
Think of it as taking the food and reducing the exposure down to an extremely tiny amount, delivered as a drop under the tongue.
The dose is very small.
The idea is to introduce the allergen gradually and give the immune system time to adapt.
In our clinic, selected patients with significant food allergy may start with SLIT before we consider moving on to oral immunotherapy.
We monitor their response and may also follow changes in skin prick test results as part of the overall assessment.
And we don’t rush.
For some patients, we may continue SLIT for at least a year before considering the next step.
OIT: Training With the Real Food
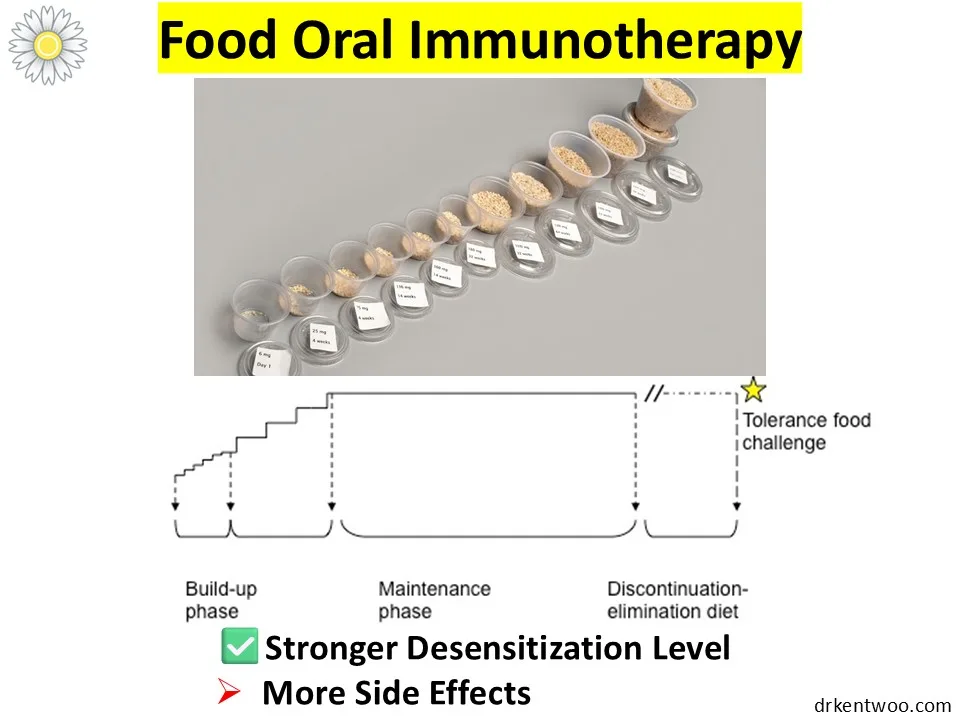
Oral Immunotherapy (OIT) is different.
Instead of tiny drops, we use the actual food allergen in carefully measured doses.
Think:
SLIT → very small exposure
OIT → the actual food, in controlled doses
The dose starts very small and is gradually increased.
The aim is to increase the amount of food a person can tolerate before reacting.
For some children, this can provide an important safety buffer against accidental exposure.
It does not mean they can simply eat the food freely.
They still need to follow their treatment plan, avoid unnecessary exposure and carry their emergency medication.
What About Side Effects?

Like exercise, immunotherapy can sometimes produce symptoms while the body is adapting.
These may include:
- Mouth or throat itching
- Stomach discomfort
- Hives
- Eczema flares
But the analogy stops there.
With exercise, people sometimes say:
“No pain, no gain.”
With food allergy:
We never simply push through an allergic reaction.
Symptoms need to be assessed carefully.
The dose may need to be adjusted, or the treatment plan changed.
This is medical training for the immune system — not something to try at home.
What If a Child Is Extremely Sensitive?
Some children react to extremely small amounts of food.
Others have multiple food allergies.
And some may find the early stages of immunotherapy difficult.
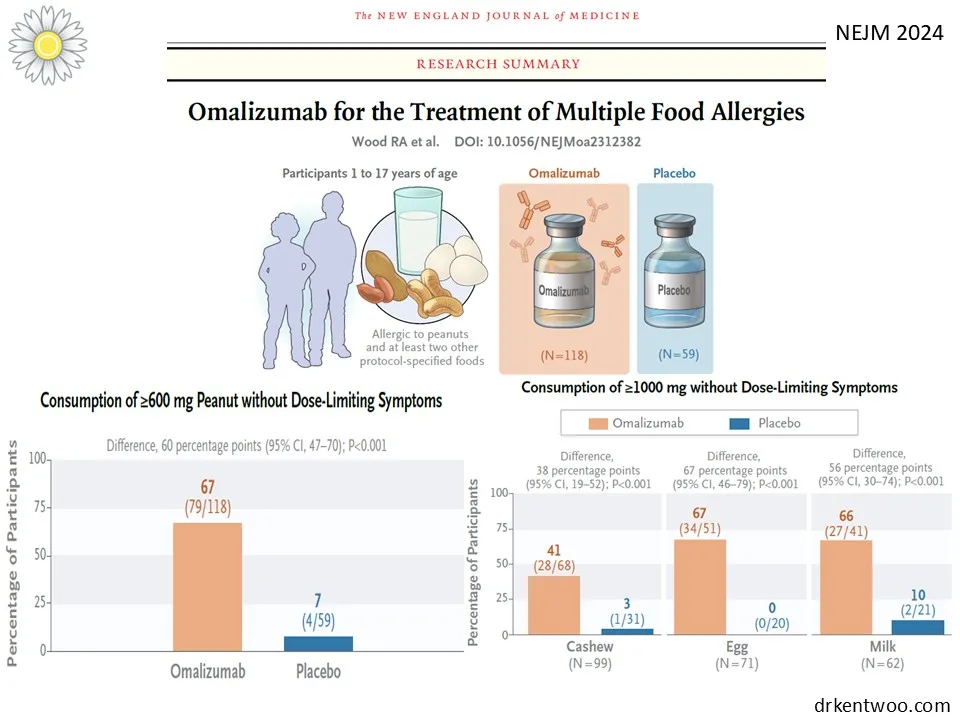
This is where omalizumab can become another tool.
Omalizumab is an anti-IgE biologic. It targets IgE, an antibody that plays an important role in allergic reactions.
It is approved for children aged 1 year and older and adults with IgE-mediated food allergy to reduce allergic reactions from accidental exposure to one or more foods.
However, patients still need to avoid their known food allergens, and omalizumab is not an emergency treatment for anaphylaxis.
In selected highly sensitive patients, we may use omalizumab support as part of an immunotherapy strategy.
It can also be considered when treating patients with multiple food allergies undergoing OIT.
The important point is that omalizumab does not make food allergy disappear overnight.
It is another tool that can help us design treatment for the right patient.
One Patient, One Plan
Not every child needs the same approach.
For some, careful avoidance and an emergency action plan remain appropriate.
For others, we may consider:
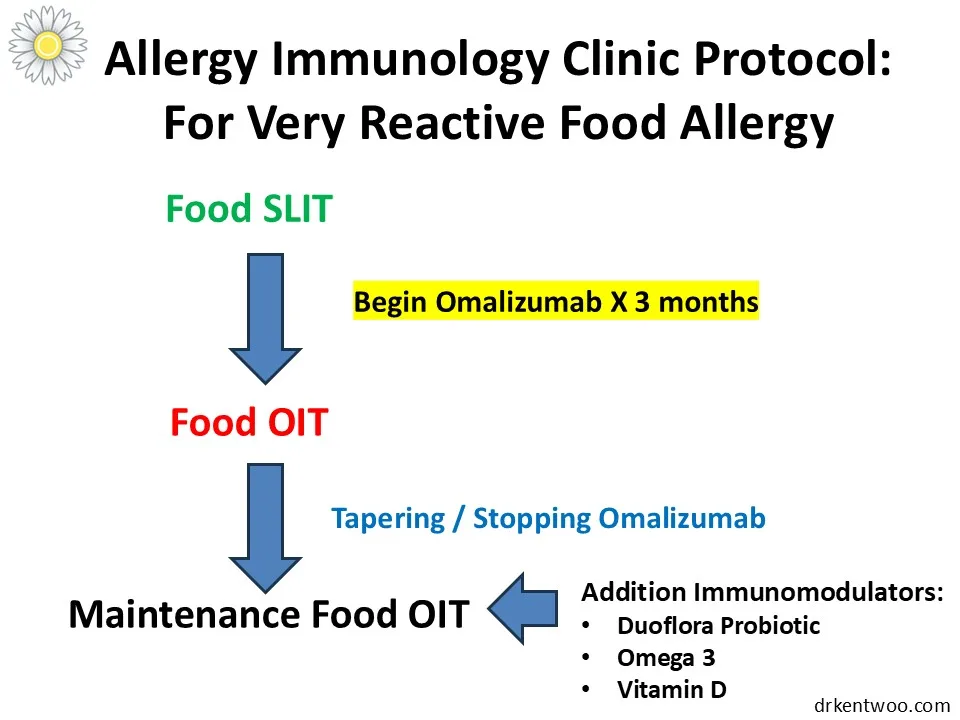
SLIT → OIT
For a highly sensitive child, omalizumab may be added as part of the treatment strategy.
For multiple food allergies, multi-food OIT with omalizumab may be considered.
The decision depends on many factors:
The child’s allergy history.
How sensitive they are.
The foods involved.
Other allergic conditions.
Their response to treatment.
Their age.
And the family’s ability to follow the treatment protocol.
There is no one-size-fits-all immunotherapy.
Desensitization — And Sometimes Tolerance
This is an important distinction.
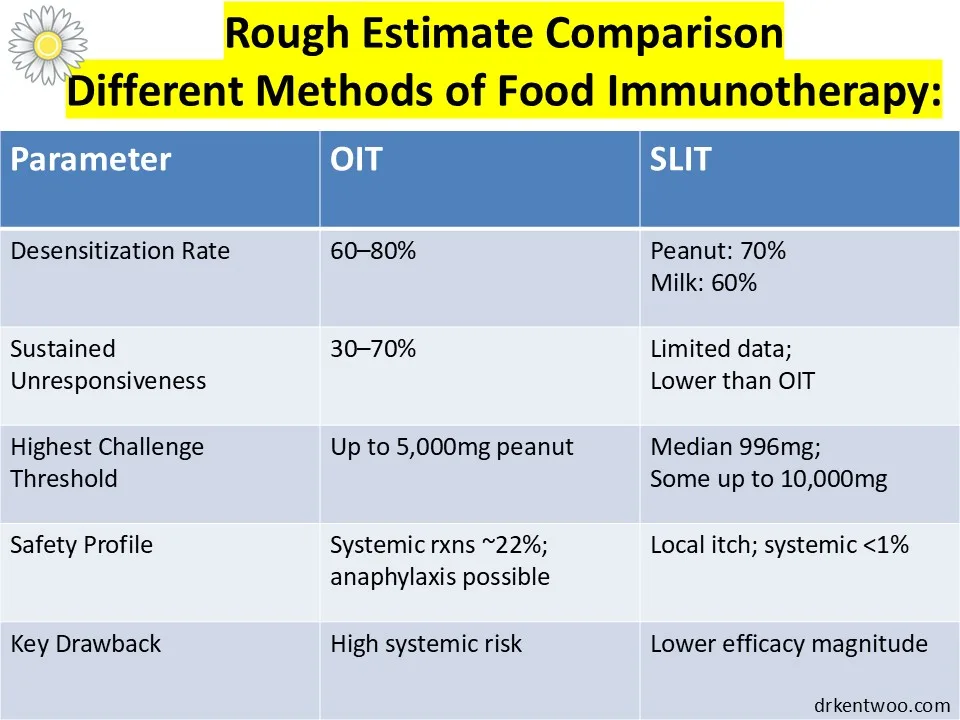
The usual goal of food immunotherapy is desensitization.
That means increasing the amount of food a person can tolerate without reacting.
For many patients, this provides a valuable safety buffer against accidental exposure.
But desensitization is not the same as a cure.
The increased tolerance often depends on continuing treatment or regular exposure according to the treatment plan.
However, this is not the whole story.
A proportion of patients may develop longer-lasting tolerance.
In other words, some patients may continue to tolerate the food even after treatment has been stopped for a period of time.
This is often described as sustained unresponsiveness or clinical tolerance. Studies have demonstrated this in some patients, although the likelihood varies between foods and individuals and the evidence is still evolving.
So I would not tell a family:
“This will absolutely cure the allergy.”
But I also would not tell them:
“The allergy can never go away.”
The reality is more nuanced.
For some children, immunotherapy may provide a useful safety buffer.
For some, it may lead to a much greater degree of tolerance.
And for a proportion of patients, that tolerance may persist beyond active treatment.
That is one of the reasons food allergy immunotherapy is such an important and evolving area of allergy care.
Food Allergy Treatment Is Changing
For many years, the question was:
“How do we avoid the food?”
Now we can also ask:
“Can we train the immune system to tolerate more?”
We have more tools than we did before.
SLIT.
OIT.
Multi-food OIT.
And, for selected patients, omalizumab.
But these treatments are not suitable for everyone.
They need careful patient selection, medical supervision and a treatment plan that fits the individual child.
The goal isn’t simply to make a child eat their allergen.
The goal is to make life with food allergy safer — and, for some patients, potentially change the allergy itself.
And sometimes, that can mean moving from:
“What happens if my child accidentally eats it?”
to:
“My child does not react to accidental exposure.”
That can be a meaningful change for a child and their family.
We care for you.
[Click here to: Learn How Duoflora Probiotic Can Help With Food Allergies]
👉 If your child has a significant food allergy and you would like to know whether food immunotherapy may be appropriate, Contact Allergy & Immunology Clinic.